


The Revenue Cycle Runs on Data It Cannot See



Hospitals spent $43 billion chasing insurance payments in 2025, on margins that averaged 1%. That arithmetic does not describe an industry with a process problem. It describes an industry with a data problem that keeps getting addressed with process solutions.
The prior authorization that takes 14.6 hours of physician time per week is not slow because the task is complex. It is slow because the clinical record lives in one system, payer policy lives in another, claims status sits in a third, and someone assembles the picture by hand every time an authorization needs to move. The denial that arrives six weeks after a claim is submitted is not a billing error. It is the downstream consequence of an incomplete picture at the point of submission. The underpayment that closes silently on a paid claim is not a reconciliation failure. It is a visibility failure.
Every one of these problems has the same root cause. The data required to prevent them exists. It simply does not exist in the same place at the same time.
What Fragmentation Actually Costs
The standard response to revenue cycle underperformance is process improvement: tighter workflows, better training, more checkpoints, additional staff. These interventions produce real improvements within individual workflows. They do not address what happens at the boundaries between workflows, where context degrades, and information that was accurate at one step becomes unavailable or incomplete at the next.
A prior authorization agent that submits faster does not prevent denials caused by documentation that was incomplete when the auth was submitted. A denial dashboard that surfaces patterns does not address the registration error that created the eligibility denial three weeks before the claim was filed. A coding tool that catches modifier errors does not surface the payer behavior shift that is now denying a procedure category it previously approved at high rates.
Each of these tools is doing its job correctly. The problem is that none of them can see outside their own workflow, and the revenue cycle's most expensive failures happen at exactly the points where one workflow hands off to the next.
Context Is the Bottleneck
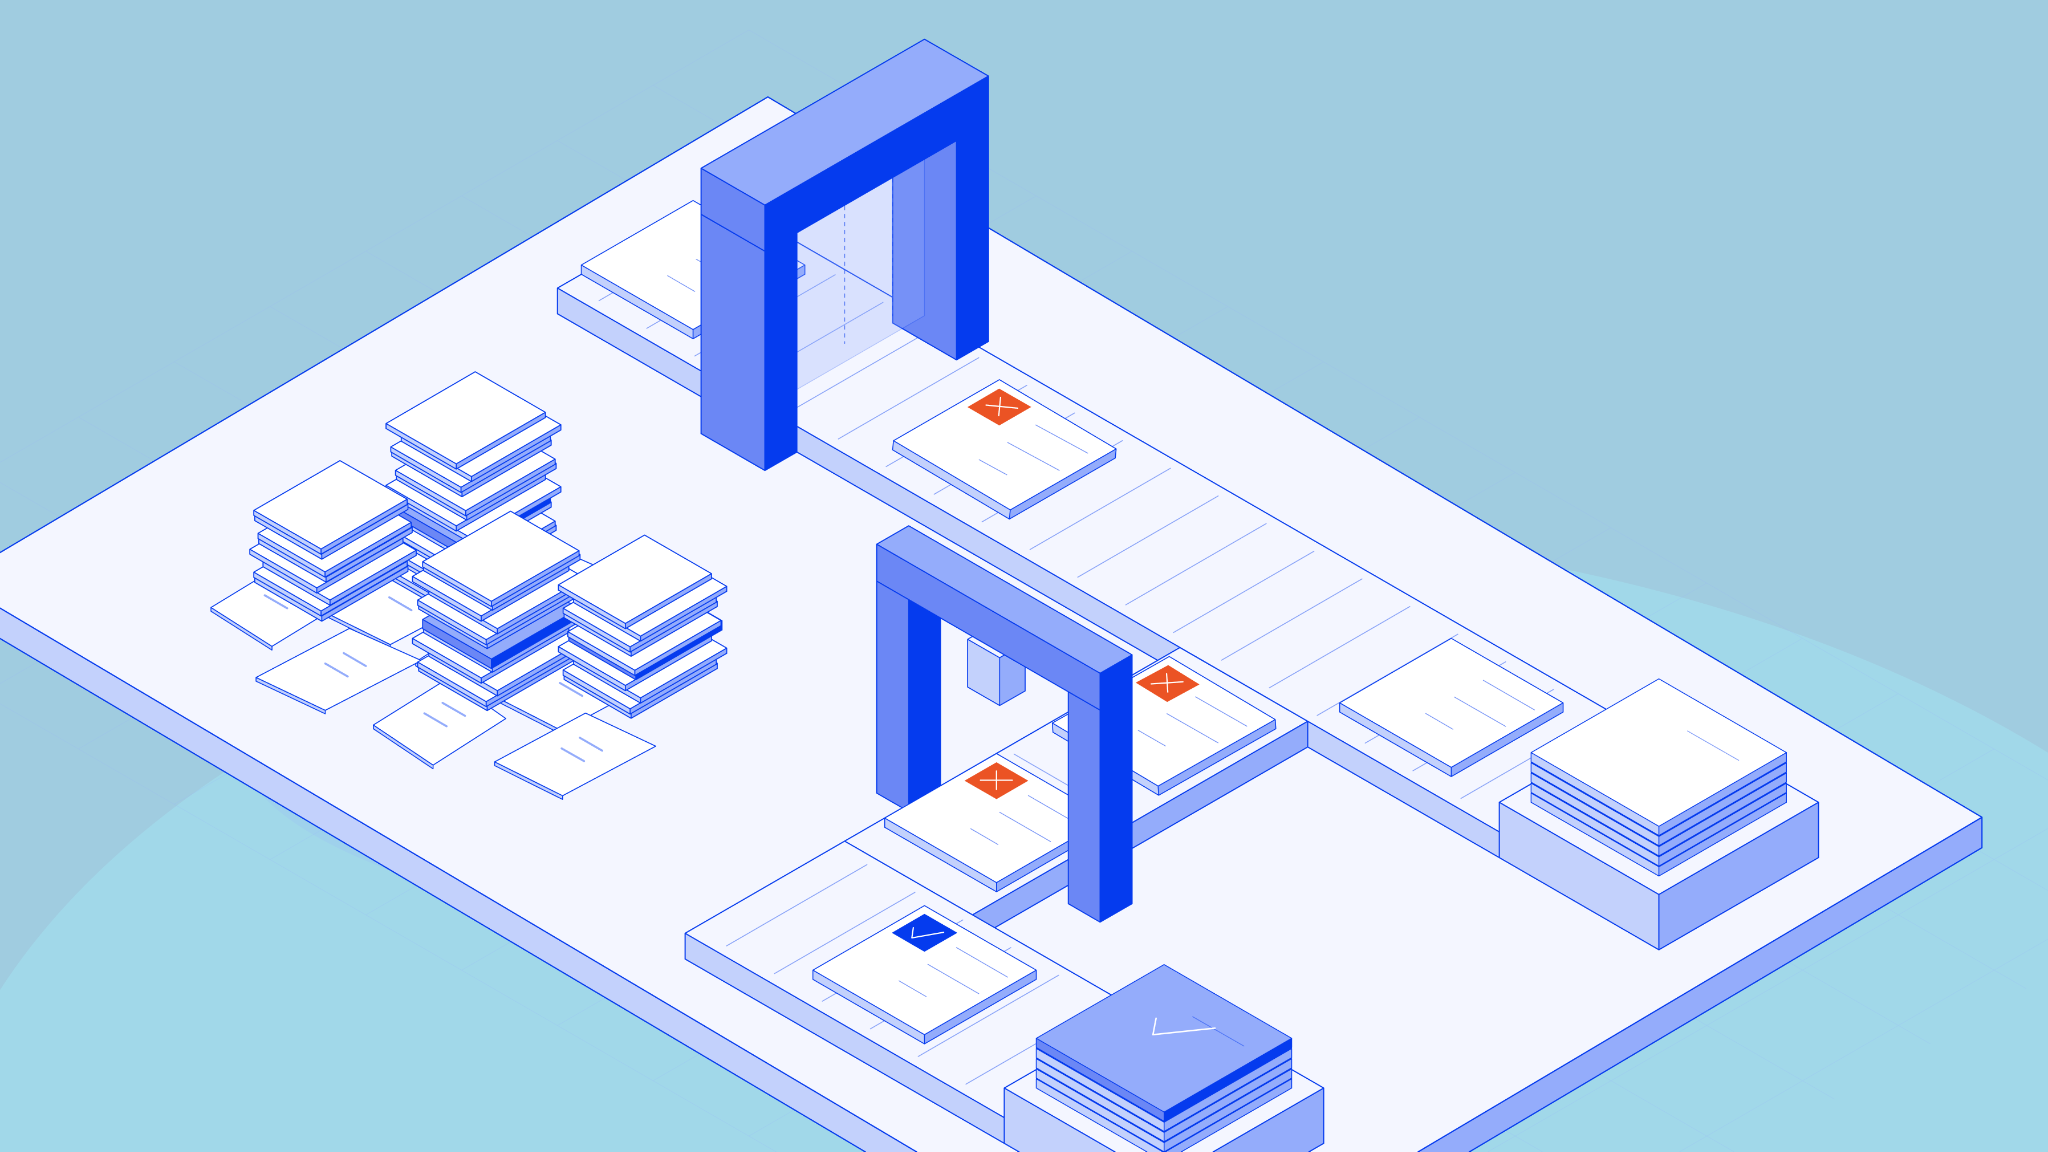
The real bottleneck in the modern revenue cycle is not capacity. Most health systems have invested heavily in automation, staffing, and tooling. The bottleneck is context, specifically the absence of a shared data layer where clinical records, payer policy, claims status, and referral documents exist together before any agent or specialist acts.
When an agent operates without that unified context, it optimizes the step it can see. When a specialist operates without it, they spend the first portion of every complex case assembling the picture manually before they can apply any judgment to it. The assembly work is not the value-add. It is the tax on getting to the value-add, and it scales with volume rather than improving over time.
The organizations closing the gap between their current revenue cycle performance and what the industry's best performers achieve are not doing it by adding more tools to the existing fragmentation. They are doing it by connecting the data first, and letting agents act on the complete picture rather than the partial one.
What a Connected Data Foundation Changes
Flow is built on a connected data foundation that brings clinical records, payer policy, claims status, and referral documents into a single context layer before any RCM AI agent acts. That foundation is not assembled at the point of need through integrations added after deployment. It is the starting condition from which every agent operates.
The practical consequence is that an agent handling prior authorization already has the clinical documentation, the payer's current criteria, and the patient's coverage status before it takes a single action. An agent working a denial already has the original authorization record, the documentation submitted with the claim, and the payer's denial pattern history for that procedure category. A specialist stepping in on a complex case finds the context already assembled rather than spending time gathering it from disconnected systems.
Through the Outcome Intelligence Loop™, every outcome feeds back into the system automatically. When a payer shifts behavior on a procedure category, the coding logic updates in real time. When a denial pattern traces back to a documentation gap at the point of care, the change happens upstream before the next case of that type creates the same result. The system does not just process revenue cycle work. It improves its own accuracy with every case it handles.
That is the structural difference between a revenue cycle that runs on data it can see and one that keeps solving the same problems because the data that would prevent them was never connected in the first place.

with the Power of Comet



